
12-Lead ECG Placement: A Step-by-Step Guide to Electrode Positioning
10/05/2026 05:11:29
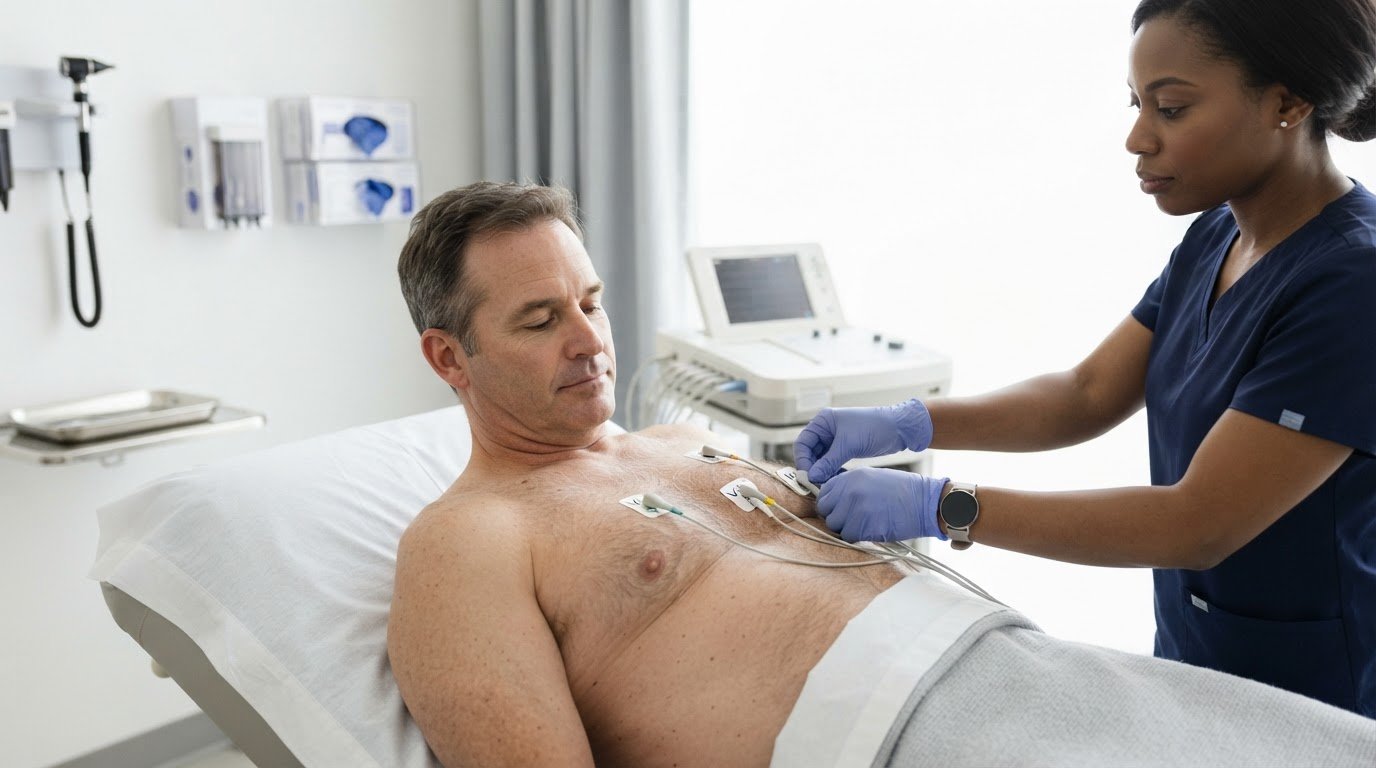
Could two chest electrodes placed too high change the story an ECG tracing tells? Yes. Incorrect positioning can affect the recorded waveform and complicate interpretation. Accurate 12 lead ecg placement depends on locating anatomical landmarks, not estimating spacing across the chest.
A standard 12-lead ECG uses 10 electrodes: four limb electrodes and six chest electrodes that produce 12 views of the heart’s electrical activity. Understanding the difference between electrodes and leads makes the setup easier to follow, while careful positioning supports a consistent tracing.
This step-by-step guide explains where to place all 10 electrodes, from the limb locations to the landmarks for V1 through V6. You’ll learn a practical setup sequence, what to check before recording, and how diagnostic ECG limb placement differs from torso placement used for continuous monitoring. We’ll also cover when to document modified placement so the tracing can be interpreted and compared with appropriate context.
Key Takeaways
- A standard 12-lead ECG records 12 electrical views using 10 electrodes, so the number of electrodes and leads is different.
- Accurate 12 lead ecg placement starts with anatomical landmarks, including the sternal borders and intercostal spaces, before positioning the chest electrodes.
- Follow the standard limb-electrode arrangement and the ECG device instructions or applicable clinical protocol.
- Use a consistent setup sequence and complete a final placement check before recording to help catch avoidable errors.
- Document modified electrode positions so clinicians have context when interpreting the tracing or comparing it with other recordings.
12-Lead ECG Placement Basics: Why 10 Electrodes Record 12 Leads
A standard ECG setup has 10 physical electrodes, but the tracing displays 12 electrical views of the heart. The distinction matters during 12 lead ecg placement: electrodes attach to the skin and detect electrical signals, while leads are views calculated from those signals. The terms are related, but they are not interchangeable.
What is the difference between ECG electrodes and leads?
An electrode is a sensor attached to the patient’s skin. It detects electrical activity and sends the signal to the ECG machine. A lead is a calculated view of that activity, based on comparisons between signals from different electrodes. The conventional 12-lead ECG uses these signals to create 12 views without requiring 12 separate sensors.
The four limb electrodes contribute to six limb leads: I, II, III, aVR, aVL, and aVF. Each of the six chest electrodes contributes a precordial lead, V1 through V6. Together, these form the 12 leads on the tracing. In practical terms, electrodes collect the signals, and the ECG system combines them to show different electrical perspectives.
Which electrodes make up a standard 12-lead ECG?
The standard arrangement includes four limb electrodes and six chest, or precordial, electrodes. Their labels identify the intended electrode:
- RA: right arm
- LA: left arm
- RL: right leg
- LL: left leg
- V1-V6: six chest electrodes positioned at specific anatomical landmarks
RA, LA, RL, and LL refer to the limb electrodes, even when a clinical protocol or monitoring setup uses modified positions. The precise location depends on whether the recording is a standard diagnostic ECG or another setup. Follow the ECG machine’s instructions and applicable clinical protocol rather than assuming the labels always indicate a particular placement point.
Display labels and abbreviations can vary by device. Before connecting electrodes, check the machine’s screen, cable markings, and instructions. This guide explains the setup and electrode groups, but it does not replace clinical training or provide a basis for independent diagnosis or interpretation. Use placement guidance to support a consistent recording, and refer questions about the tracing to an appropriately qualified professional.
How to Place the Six Chest Electrodes at the Correct Landmarks
Accurate chest-electrode positioning starts with anatomy, not guessed spacing. Prepare the patient and expose the chest as appropriate, then identify the sternal borders and count the intercostal spaces before attaching electrodes. Using landmarks helps prevent electrodes from being placed too high or too low.
Where do V1, V2, and V4 go?
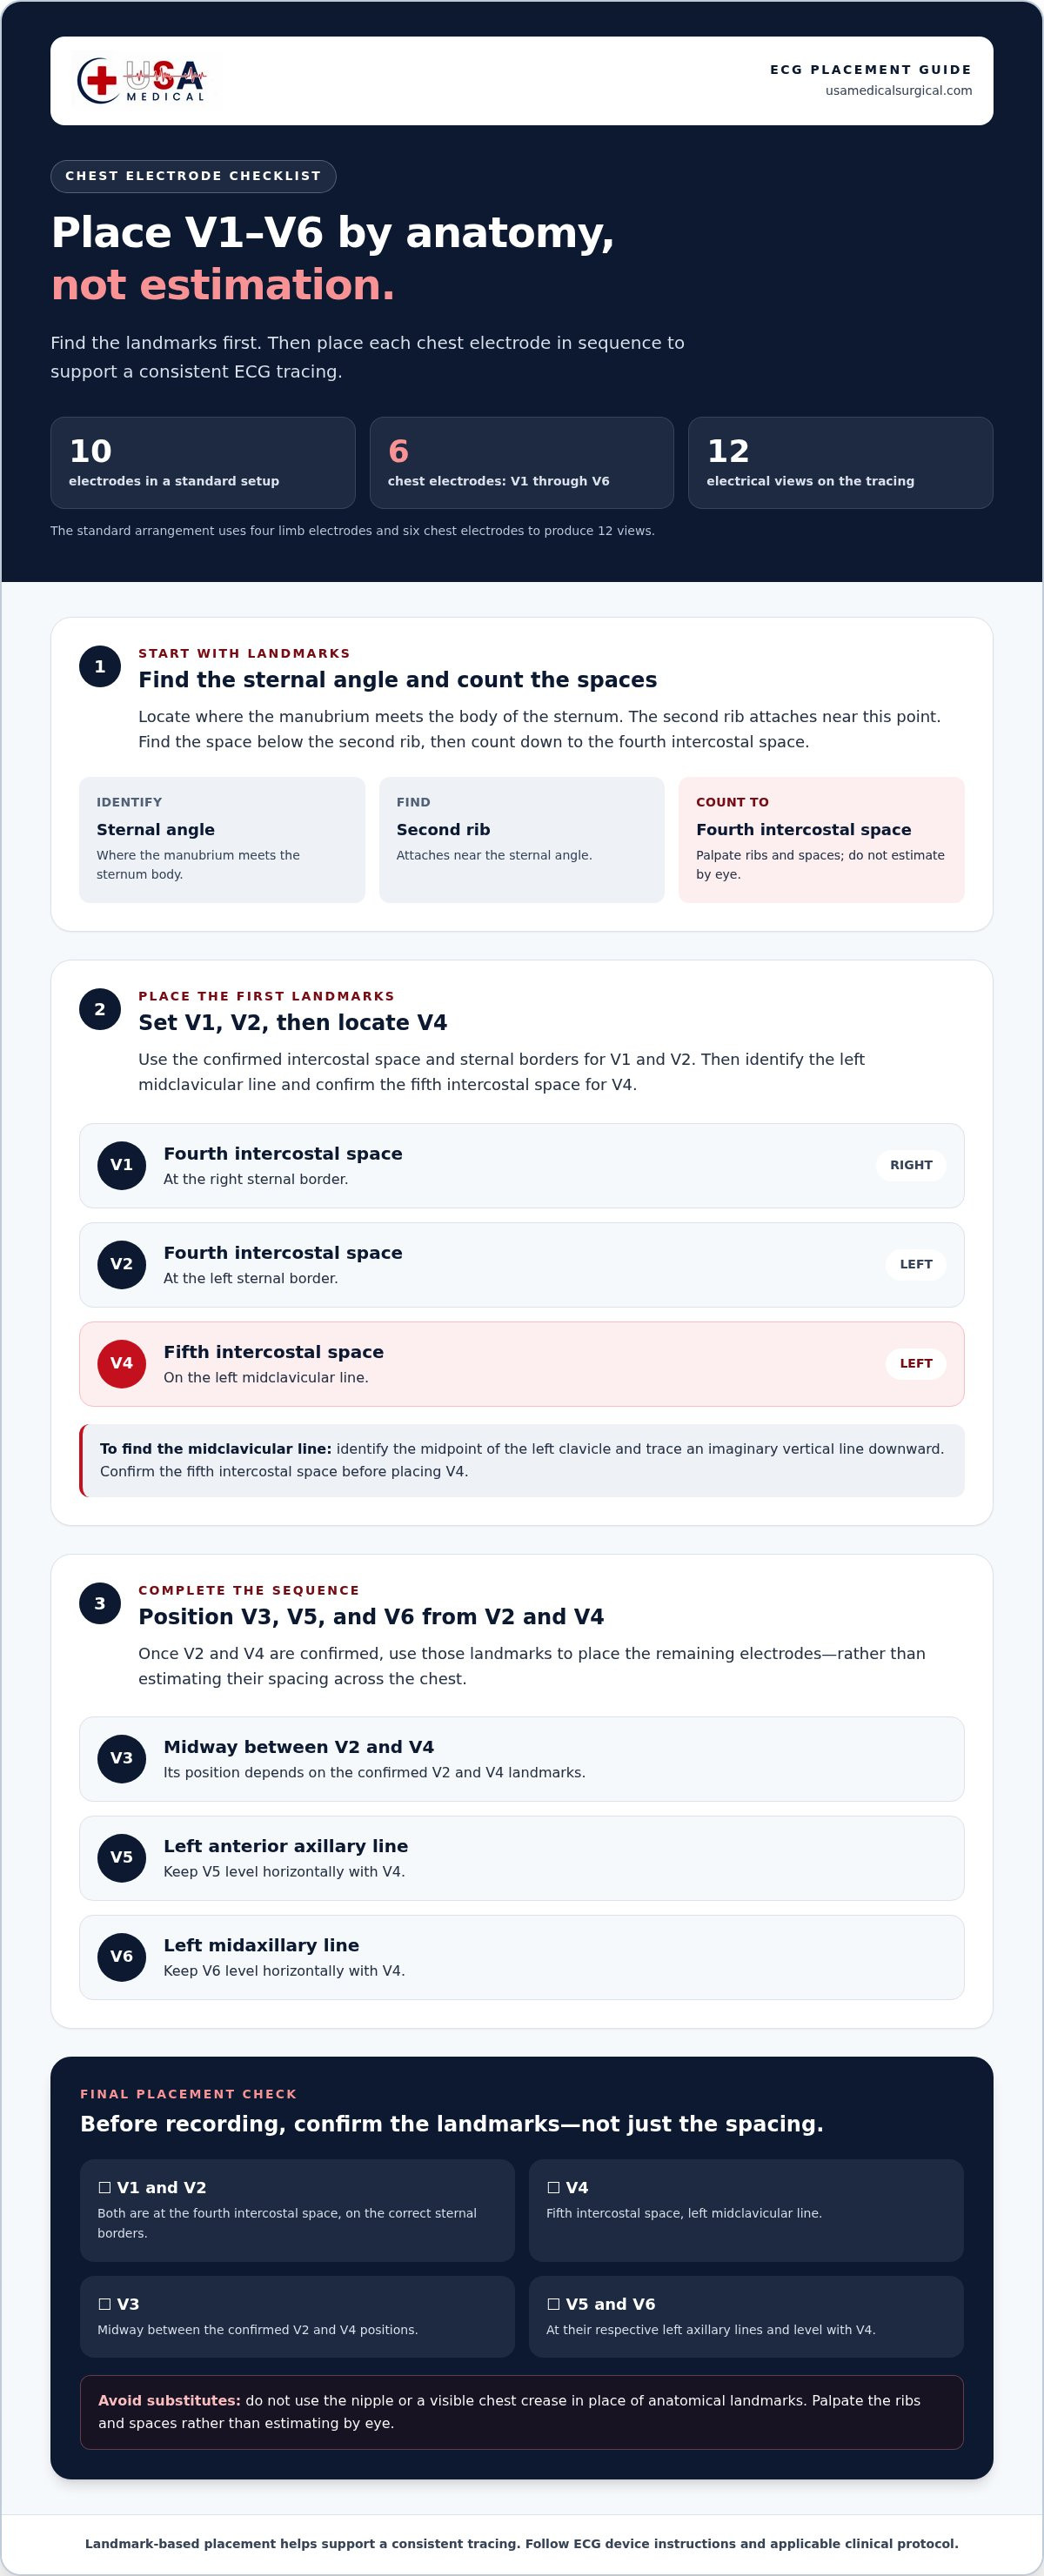
Locate the sternal angle, where the manubrium meets the body of the sternum. The second rib attaches near this landmark. Find the space just below the second rib, then count down to the fourth intercostal space. Palpate the ribs and spaces rather than estimating by eye.
- V1: Fourth intercostal space at the right sternal border.
- V2: Fourth intercostal space at the left sternal border.
- V4: Fifth intercostal space on the left midclavicular line.
To find the midclavicular line, identify the midpoint of the left clavicle and trace an imaginary vertical line downward. Confirm the fifth intercostal space before placing V4. Do not use the nipple or a visible chest crease as a substitute for the anatomical landmark.
How do you position V3, V5, and V6?
After locating V2 and V4, place V3 midway between them. V3’s position depends on the confirmed V2 and V4 landmarks, not on an estimated progression across the chest. Next, place V5 on the left anterior axillary line and V6 on the left midaxillary line. Keep both level horizontally with V4.
Standard V1-V6 landmarks: V1, fourth intercostal space at the right sternal border; V2, fourth intercostal space at the left sternal border; V3, midway between V2 and V4; V4, fifth intercostal space at the left midclavicular line; V5, level with V4 at the left anterior axillary line; and V6, level with V4 at the left midaxillary line.
A reliable sequence is to locate V1 and V2, identify V4, then position V3 and place V5 and V6 at the same horizontal level as V4. This landmark-based approach supports consistent 12 lead ecg placement. For a visual reference to precordial lead placement, consult LITFL’s clinical guide.
Use ECG electrodes suited to the recording setup and follow the device instructions for application. Browse ECG electrodes and equipment for supplies for ECG recording.
Limb Electrode Placement and Standard Versus Modified Positions
The four limb electrodes provide signals used to create the six limb leads. For a standard diagnostic ECG, place them on the limbs according to the ECG machine’s instructions and applicable clinical protocol. Correct limb-electrode positioning is an essential part of consistent 12 lead ecg placement. Identify each site by its label rather than relying on wire color alone.
Where should RA, LA, RL, and LL be placed?
RA and LA are assigned to the right and left arms; RL and LL are assigned to the right and left legs. For a standard diagnostic recording, limb electrodes are placed on the limbs, typically at distal sites such as the wrists or lower legs. Follow the device instructions and local protocol for the precise positions, and match each electrode to the correct limb using the cable labels.
- RA: right arm
- LA: left arm
- RL: right leg
- LL: left leg
The RL electrode has a supporting role in the recording setup. It is commonly used as a ground or reference to help reduce electrical interference; it is not one of the six limb leads displayed on the tracing. Color coding can differ between devices and standards, so confirm the RA, LA, RL, and LL markings on the lead wires instead of assuming a color always identifies the same electrode.
When might limb electrode positions be modified?
Clinical circumstances or a specific protocol may call for moving limb electrodes to the torso. This modified arrangement is commonly used for continuous monitoring when movement makes limb placement less practical or contributes to artifact. It is not interchangeable with standard limb placement for a diagnostic ECG. Moving electrodes changes the electrical viewpoints and may alter waveform appearance, which can affect comparison with a tracing made using standard positions.
Use the placement required for the intended recording and follow local clinical protocol. If electrodes are placed in nonstandard positions, document the variation clearly, including the sites used, so the person interpreting the tracing has that context. Documentation also helps clinicians assess differences between recordings made with different electrode positions.
Before recording, check each limb label, confirm that the electrodes are attached to the intended sites, and note any required modification. Consistent setup and clear documentation make ECG recordings easier to interpret and compare. They also help distinguish a change in electrode position from a change in the patient’s electrical pattern.
A Step-by-Step 12-Lead ECG Placement Check Before Recording
A repeatable setup sequence helps staff check preparation, electrode locations, and connections before recording. Follow the ECG device instructions, electrode packaging, and your clinical setting’s protocol throughout. This checklist supports accurate 12 lead ecg placement, but it does not replace clinical training or interpretation.
How should the patient and skin be prepared?
Explain the setup, provide appropriate privacy, and position the patient comfortably with the body supported. Arrange access to the chest and limbs while maintaining dignity and following the setting’s standard procedure. Prepare the skin only as directed by the electrode packaging and device instructions. Different electrodes or equipment may have specific application guidance, so do not assume the same preparation method suits every setup.
- Prepare the equipment and space. Confirm that the ECG machine is ready for use and gather the electrodes required for the recording. Check the packaging and device instructions before application.
- Position the patient. Provide privacy and support a comfortable, stable position consistent with the clinical protocol. Make sure the areas needed for electrode placement are accessible.
- Identify the landmarks. Locate the required chest and limb sites using anatomical references and the established placement sequence. Do not estimate chest locations by eye when you can identify the landmarks.
- Attach and connect electrodes. Match each electrode to the device’s labels, place it at the intended site, and check that it makes secure contact with the skin. Keep cables connected to their corresponding labels.
- Complete a final review. Before recording, confirm the electrode labels, anatomical locations, cable connections, and skin contact. Check that the patient is comfortable and can remain as still as practical during acquisition.
What should you check if the tracing looks unusual?
Pause and review the setup instead of assuming the tracing reflects a placement problem or a clinical finding. Recheck electrode labels, cable connections, and anatomical landmarks. Look for movement, loose electrodes, or other visible recording artifacts. These checks can help identify setup issues, but they do not determine the cause of an unusual tracing.
Follow local clinical protocol for repeating a recording or escalating a questionable result. If electrode positions were modified, make sure the variation is documented so it can be considered during interpretation and comparison with other recordings.
Final check: Are the labels matched correctly? Are the electrodes on the intended landmarks? Is each electrode in secure contact? If any answer is uncertain, follow the device instructions and clinical protocol before recording.
Browse ECG electrodes and equipment for ECG setup supplies.
Reliable ECG Setup: Documentation, Supplies, and Next Steps
Reliable 12 lead ecg placement depends on three habits: identify the landmarks, follow the placement sequence, and verify each electrode before recording. A clear record of the setup adds useful context, especially when electrode positions differ from the standard arrangement.
What should be documented when placement differs?
Follow facility policy and clinical protocol for documenting modified or nonstandard electrode positions. Record the variation clearly enough that another qualified professional can understand how the tracing was obtained. Consistent notes are particularly useful when comparing serial ECG recordings, since a difference in electrode position may affect how the tracings look.
Documentation provides context; it does not determine what a tracing means. Leave clinical interpretation and decisions to qualified professionals, and escalate questions through the appropriate clinical process.
How do electrodes and ECG equipment support a consistent setup?
ECG electrodes are a practical part of the recording workflow. Use electrodes compatible with the ECG equipment, and check the device instructions for connector, lead-wire, and setup requirements. Matching electrodes and connections correctly supports an orderly setup, but does not replace landmark checks or the final placement review.
Keep the equipment instructions and electrode packaging accessible during setup. If you’re evaluating ECG equipment for your workflow, explore the ECG machine buying guide for practical considerations when selecting a device.
Before recording, confirm the electrode labels and sites, check for secure contact, and note any placement variation according to local procedure. This simple review supports consistent documentation and gives the next reader essential context for understanding and comparing the recording.
Make Each ECG Setup Consistent
Accurate 12 lead ecg placement comes down to a clear process: locate anatomical landmarks, follow the electrode sequence, and verify each connection before recording. Remember that 10 electrodes generate 12 electrical views. For a standard diagnostic ECG, use standard limb positions. If clinical circumstances require a modified setup, document the variation according to local protocol.
A final check of electrode labels, placement, and skin contact can help catch avoidable setup issues. Follow the ECG machine and electrode instructions, and leave interpretation and clinical decisions to qualified professionals.
USA Medical and Surgical Supplies offers ECG machines and ECG electrodes. Browse ECG equipment and supplies to explore options for your recording workflow.
Careful landmark checks and consistent documentation help make each setup clearer and more repeatable.
Frequently Asked Questions
Where exactly do you place the electrodes for a 12-lead ECG?
A standard 12-lead ECG uses four limb electrodes and six chest electrodes. Place V1 at the fourth intercostal space at the right sternal border, V2 at the fourth intercostal space at the left sternal border, and V4 at the fifth intercostal space on the left midclavicular line. Position V3 between V2 and V4, then place V5 and V6 level with V4 at the anterior and midaxillary lines. Follow device instructions and clinical protocol for limb sites.
Why does a 12-lead ECG use only 10 electrodes?
A 12-lead ECG uses 10 skin electrodes to calculate 12 electrical views of the heart. The four limb electrodes generate six limb leads, while the six chest electrodes provide six precordial leads. A lead is not a separate sensor; it is a view derived from electrode signals. The ECG machine combines those signals to display the tracing. That is why the number of leads differs from the number of electrodes attached to the patient.
Where do V1 and V2 go on an ECG?
Place V1 in the fourth intercostal space at the right sternal border and V2 in the fourth intercostal space at the left sternal border. To find the fourth space, locate the sternal angle, identify the second rib, then count down the spaces between the ribs. Palpate the landmarks instead of estimating by eye. Correct V1 and V2 positioning is an important part of accurate 12 lead ecg placement.
How do you find the correct position for V4, V5, and V6?
Place V4 in the fifth intercostal space on the left midclavicular line. Find the midpoint of the clavicle and trace an imaginary vertical line down to the fifth space. Place V5 on the left anterior axillary line and V6 on the left midaxillary line, both level horizontally with V4. Locate V4 first, then use its horizontal level to guide V5 and V6.
Can limb electrodes be placed on the torso instead?
Torso placement may be used for continuous monitoring when clinical circumstances or local protocol call for it, but it is not interchangeable with standard limb placement for a diagnostic ECG. Moving the electrodes can change the waveform and affect comparisons with recordings made using standard positions. Follow the protocol for the recording, and document any modified sites so qualified clinicians have the necessary context for interpretation.
What happens if ECG electrodes are placed incorrectly?
Incorrect electrode placement can change the waveform and affect manual or automated interpretation. The tracing may not show the expected electrical views, which can complicate comparison with prior recordings. If the tracing looks unusual, recheck electrode labels, cable connections, anatomical landmarks, and electrode contact. Follow clinical protocol for repeating or escalating a questionable recording. Placement checks support setup accuracy but do not replace professional interpretation.
Do you need to prepare the skin before applying ECG electrodes?
Prepare the skin as directed by the electrode packaging, ECG device instructions, and clinical protocol. Make sure the intended sites are accessible and the electrodes can make secure contact with the skin. Preparation steps can depend on the equipment and electrodes, so do not assume one method applies to every setup. Maintain patient privacy and comfort, and follow your facility’s standard procedure for skin access and preparation.